

| Sooyoung Cho | 6 Articles |
|
[English]
Purpose
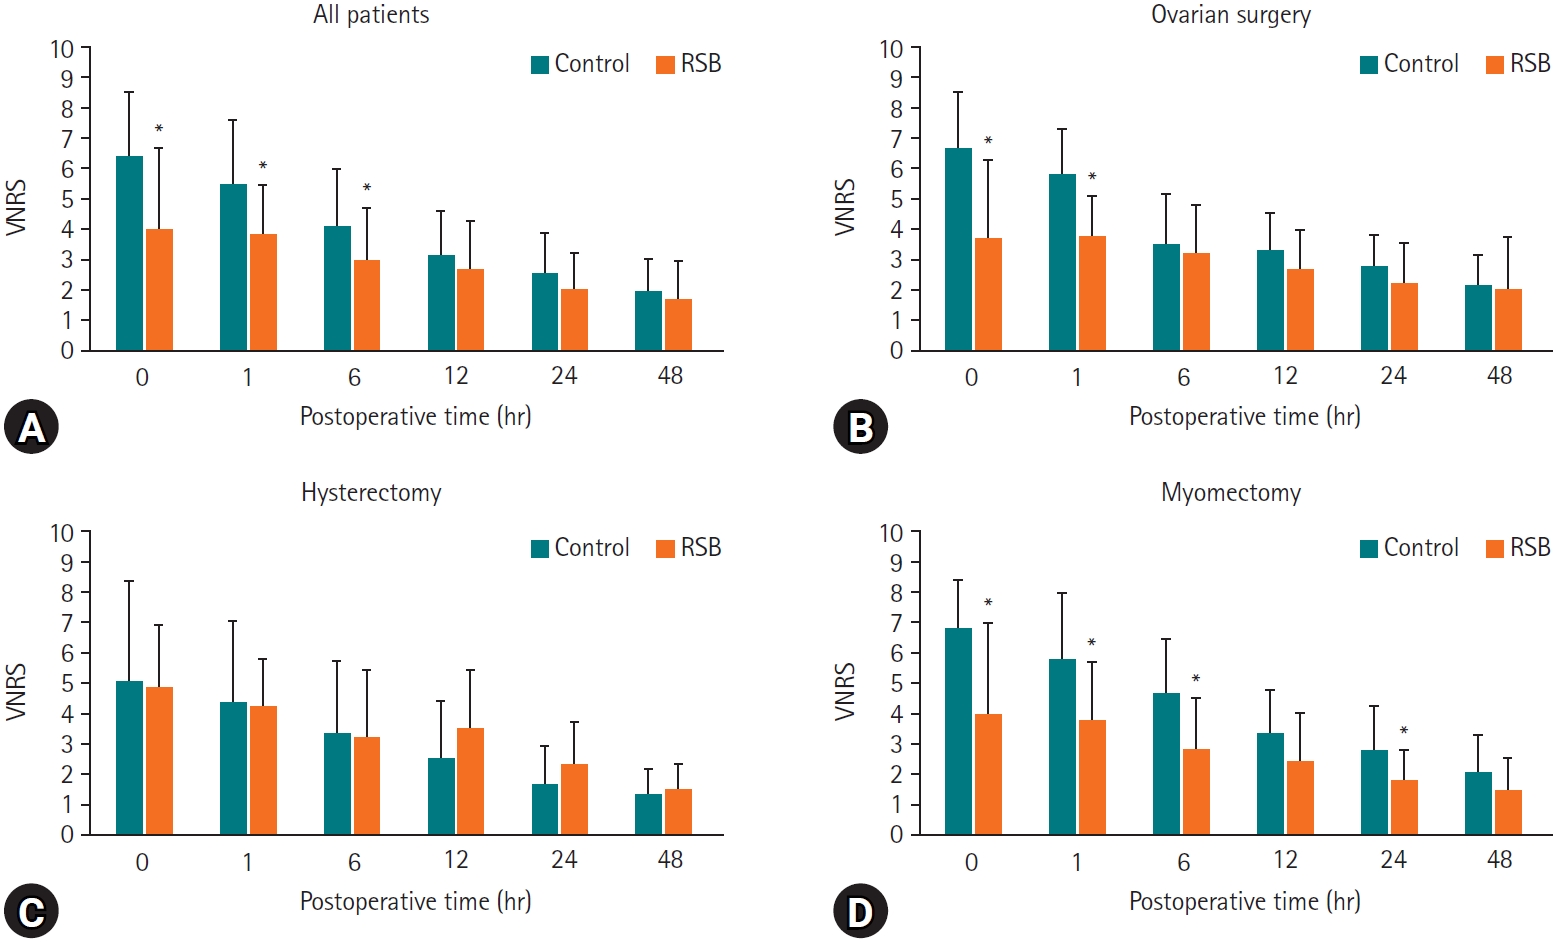
Rectus sheath block (RSB) is a simple abdominal wall block that can be readily applied. This study evaluated the postoperative analgesic efficacy of ultrasound-guided bilateral RSB in robotic single-site gynecologic surgery. Methods Sixty patients were randomly assigned to the RSB group (n=30) or the control group (n=30). After induction of general anesthesia, patients in the RSB group received ultrasound-guided bilateral RSB with 30 mL of 0.25% ropivacaine. Pain intensity was assessed using a verbal numerical rating scale (VNRS) at 0, 1, 6, 12, 24, and 48 hours postoperatively. Intravenous patient-controlled analgesia was provided to all patients, and fentanyl was administered as rescue analgesia on request. Results VNRS scores at 0, 1, and 6 hours were significantly lower in the RSB group than in the control group (all P<0.05). Rescue fentanyl use in the post-anesthesia care unit was also significantly lower in the RSB group than in the control group (19.8±21.0 μg vs. 46.3±27.6 μg, P<0.001). Subgroup analysis showed that RSB was associated with lower VNRS scores in patients undergoing ovarian surgery or myomectomy, whereas no significant difference was observed in patients undergoing hysterectomy. Conclusion Ultrasound-guided bilateral RSB reduced early postoperative pain and rescue analgesic requirements after robotic single-site gynecologic surgery.
[English]
Citations Citations to this article as recorded by

[English]
OxyMask, a novel product, has recently been used to administer oxygen postoperatively to patients who have undergone general anesthesia. This study aimed to evaluate the incidence of hypoxia in patients under general anesthesia upon arrival to the post-anesthesia care unit (PACU) using arterial blood gas analysis, and to compare the effectiveness of OxyMask with a non-rebreathing oxygen mask for oxygen administration. We retrospectively investigated anesthesia-related data from the electronic medical records of 460 patients treated from April to November 2021. We analyzed patients aged 20 years or older who had undergone general anesthesia and whose perioperative arterial blood gas analysis results were available upon arrival to the PACU. These patients were grouped into the non-rebreathing oxygen mask (n=223) and OxyMask (n=237) groups, and statistical analysis was performed utilizing their anesthesia records. No patients exhibited hypoxia upon arrival to the recovery room. The oxygen concentration increased after oxygen administration; its concentration during the recovery room period (Δ2 PaO2) was 10.7±42.3 and 13.9±38.5 mmHg in the non-rebreathing oxygen mask and OxyMask groups, respectively. This difference was not statistically significant. Moreover, the arterial oxygen saturation between the end of surgery and upon arrival to the PACU (Δ1 SaO2) and the arterial oxygen saturation 20 minutes after oxygen administration at the PACU (Δ2 SaO2) did not significantly differ between the groups. OxyMask was not superior to a non-rebreathing oxygen mask in terms of the effectiveness of oxygen supply.
[English]
ABSTRACT
Variant angina, which is associated with coronary artery spam, is difficult to recognize on routine preoperative evaluation. Coronary spasm results in myocardial ischemia and even lethal arrhythmia in severe cases. Since patients are unconscious and cannot complain of symptoms during general anesthesia, early detection of such an event is difficult, and it could lead to severe bradycardia or cardiac arrest. We report a case of a patient with previously undiagnosed variant angina who experienced severe hypotension and ventricular fibrillation during general anesthesia. Citations Citations to this article as recorded by
[English]
Purpose
Lipid emulsion is the only specific antidote for local anesthetic systemic toxicity, but no dose-finding study has been conducted. We compared 3 published regimens and alternative schedules that deliver the same dose in different ways using a human model of intravenous bupivacaine overdose. Methods A 14-compartment human bupivacaine model was independently reimplemented without fitted parameters, replacing first-order lipid elimination with a saturable term. Toxicity was modeled as 112.5 mg administered intravenously over 3 minutes. Benefit was defined as the predicted maximum decrease in myocardial bupivacaine within 30 minutes, and harm as the predicted relative lipid load, indexed by peak plasma triglyceride concentration. Neither measure is a validated surrogate. Results The 3 guidelines specify the same doses but different bolus durations: 1 minute versus 2–3 minutes. At a matched dose of 12 mL/kg, myocardial bupivacaine decreased by 30.5% with the 1-minute bolus and 24.9% with the 2.5-minute bolus, with the same lipid load. The completed American Society of Regional Anesthesia and Pain Medicine regimen (7.64 mL/kg) achieved a 24.6% decrease versus 24.9% with 12 mL/kg; thus, complete regimens differ in schedule as well as dose. Repeating the 1-minute bolus twice, for a total of 4.5 mL/kg, achieved a 31.9% decrease with 62% less emulsion. Start time had the greatest effect: the best regimen achieved a 41.8% decrease when started at the end of the injection, but only 9.6% when started at 10 minutes. Conclusion In this bupivacaine model, bolus duration distinguished the regimens more than dose did, and delay had a greater effect than either, eliminating most of the benefit without changing the lipid load. Treatment should begin at the first signs of toxicity, and 20% lipid emulsion should be immediately available wherever local anesthetics are used.
[English]
Sugammadex is increasingly used as the primary antagonist for rocuronium-induced neuromuscular blockade and has reduced, but not eliminated, residual paralysis. A small but continuing series of reports describes a different failure: adequate recovery of the train-of-four ratio followed by a secondary decline in neuromuscular function, sometimes more than an hour later and occasionally after a recommended dose. Sugammadex encapsulates rocuronium in a 1-to-1 ratio, and binding occurs only in plasma. Sustained reversal therefore depends on the molar relationship between the administered dose and the rocuronium remaining in the body, rather than on the milligram-per-kilogram dose. At or above molar equivalence, no uncaptured rocuronium remains, and recurrence is mechanistically excluded while free sugammadex remains in excess; below equivalence, a free fraction persists whose effect is the product of that fraction and the residual burden. A weight-based dose is fixed, whereas the burden varies, concentrating risk where the burden is large or the dosing weight is small: prolonged infusions and repeated boluses, deep block, advanced age, renal impairment, and ideal-body-weight dosing in obesity. Randomized dose-finding trials reported recurrent block almost exclusively in the lowest-dose groups, and a dosing-weight trial reproduced it by reducing the dose alone. Neither 2023 guideline addresses dosing after prolonged infusion or the duration of subsequent observation. Reported events have occurred up to about 100 minutes after reversal, usually without quantitative monitoring. We propose estimating the burden, dosing above equivalence with a margin for uncertainty, and continuing measurements beyond the first confirmed recovery.
|
|
 , Sooyoung Cho, Youn Jin Kim, Seunghee Yoo, Jong Wha Lee, Hye-Won Oh, Eunbi Cho

